
 English
 French
 Pubmed
 Google Scholar
 Cross Ref
 Visistor: 1968577
Maxillary Sinus Fungus Ball: Clinical Presentation, Computed Tomography Features, and Surgical Management: A Five-Patient Case Series
Boule Fongique du Sinus Maxillaire: Présentation Clinique, Caractéristiques Tomographiques et Prise en Charge Chirurgicale: Une Série de Cinq Cas
Diep Le-Van¹, Trang Nguyen-Minh¹, Hien Duong-Thi-Thu¹, Khanh Le-Xuan¹, Anh Luu-Thi-Van¹, Chung Tran-Nam², Phap Tran-Quang2, Tuyen Hoang-Thanh2, Sy Duong-Quy2,3
1Ear-Nose-Throat Department. 199 Hospital. Da Nang, Vietnam
2Expert Consultation Department. 199 Hospital. Da Nang, Vietnam
3Bio-Medical Research Center and Basic Science. Lam Dong Medical College. Lam Dong, Vietnam
Corresponding author: Sy Duong-Quy. Sleep Medicine Research Center. Vietnam Society of Sleep Medicine. Lam Dong, Viet Nam. Email: sduongquy.jfvp@gmail.com
ABSTRACT
Background. Maxillary sinus fungus ball (MSFB) is a non-invasive form of fungal rhinosinusitis characterized by an accumulation of fungal material within the sinus lumen without tissue invasion. Clinical manifestations are often non-specific, whereas computed tomography (CT) may provide important diagnostic clues.
Methods. We describe five patients with clinical and radiological findings suggestive of MSFB who underwent endoscopic sinus surgery. Clinical manifestations, nasal endoscopic findings, CT features, histopathological and/or mycological results, and surgical management were reviewed.
Results. The patients ranged from 29 to 66 years of age. All lesions were unilateral and involved the maxillary sinus. Purulent nasal discharge and headache were the predominant symptoms. CT demonstrated maxillary sinus opacification or mucosal thickening associated with intralesional calcifications in all patients. All patients underwent endoscopic maxillary sinus surgery. Fungal culture was negative in three patients and positive for filamentous fungi in one patient; histopathological examination in the remaining patient showed inflammatory tissue.
Conclusions. MSFB should be considered in persistent unilateral maxillary sinus disease, particularly when CT demonstrates intralesional hyperattenuation or calcification. Negative fungal culture does not exclude MSFB. Diagnosis should integrate clinical, endoscopic, radiological, intraoperative, histopathological, and mycological findings. Endoscopic sinus surgery remains the treatment of choice for symptomatic disease.
KEYWORDS: Maxillary sinus fungus ball; Fungal rhinosinusitis; Computed tomography; Endoscopic sinus surgery.
RÉSUMÉ
Contexte. La boule fongique du sinus maxillaire (BFSM) est une forme non invasive de rhinosinusite fongique caractérisée par l'accumulation de matériel fongique dans la lumière sinusienne sans invasion tissulaire. Les manifestations cliniques sont souvent non spécifiques, tandis que la tomographie computée (CT) peut fournir des indices diagnostiques importants.
Méthodes. Nous décrivons cinq patients présentant des signes cliniques et radiologiques évocateurs d'une BFSM ayant bénéficié d'une chirurgie endoscopique sinusienne. Les manifestations cliniques, les résultats de l'endoscopie nasale, les caractéristiques scannographiques, les résultats histopathologiques et/ou mycologiques, ainsi que la prise en charge chirurgicale ont été examinés.
Résultats. Les patients étaient âgés de 29 à 66 ans. Toutes les lésions étaient unilatérales et touchaient le sinus maxillaire. L'écoulement nasal purulent et les céphalées étaient les symptômes prédominants. La tomographie a mis en évidence une opacification du sinus maxillaire ou un épaississement muqueux associé à des calcifications intralésionnelles chez tous les patients. Tous ont eu une chirurgie endoscopique du sinus maxillaire. La culture fongique était négative chez trois patients et positive pour des champignons filamenteux chez un patient; l'examen histopathologique chez le dernier patient a révélé un tissu inflammatoire.
Conclusions. La BFSM doit être suspectée en cas de pathologie sinusienne maxillaire unilatérale persistante, en particulier lorsque le scanner montre une hyperatténuation ou des calcifications intralésionnelles. Une culture fongique négative n'exclut pas le diagnostic. Le diagnostic doit intégrer les données cliniques, endoscopiques, radiologiques, peropératoires, histopathologiques et mycologiques. La chirurgie endoscopique sinusienne reste le traitement de choix pour la maladie symptomatique.
MOTS CLÉS: Boule fongique; Rhinosinusite fongique; Chirurgie endoscopique.
INTRODUCTION
Fungal rhinosinusitis encompasses a heterogeneous spectrum of sinonasal disorders with distinct clinical, radiological, microbiological, and histopathological characteristics. It is conventionally classified into invasive and non-invasive forms according to the presence or absence of fungal invasion into the sinonasal mucosa, blood vessels, bone, or surrounding tissues [1–3]. A paranasal sinus fungus ball (PSFB) is a distinct non-invasive form characterized by the accumulation of densely packed fungal hyphae within a sinus cavity without tissue invasion [2–4]. The disease generally occurs in immunocompetent adults and predominantly involves a single paranasal sinus. The maxillary sinus is the most frequently affected site, followed by the sphenoid sinus [4–6].
Clinical manifestations are often non-specific and may include unilateral nasal obstruction, purulent nasal or postnasal discharge, facial pain or pressure, headache, and olfactory disturbance [1,4,5]. Some patients are minimally symptomatic, and the lesion may be detected incidentally. This clinical heterogeneity may delay diagnosis and lead to repeated courses of medical therapy for presumed bacterial or inflammatory rhinosinusitis. Persistent unilateral maxillary sinus disease therefore deserves particular attention. In addition to fungus ball, the differential diagnosis includes chronic inflammatory rhinosinusitis, odontogenic sinusitis, foreign bodies, mucoceles, benign neoplasms, and malignant disease.
Computed tomography (CT) plays a central role in the diagnostic work-up. Typical findings include partial or complete opacification of the affected sinus associated with intralesional hyperattenuating foci or calcifications [7,8]. These radiological abnormalities may substantially increase suspicion of a fungus ball but are not independently diagnostic. CT findings should therefore be integrated with nasal endoscopy, intraoperative appearance, histopathological examination, and mycological assessment [4].
An additional consideration in maxillary sinus fungus ball is its relationship with odontogenic factors. Endodontic procedures, dental pathology, root-canal filling materials, and dental implants have increasingly been associated with selected cases of MSFB [9,10]. CT studies have further suggested an association between metal-type intralesional hyperdensities and previous endodontic treatment [10]. More recent evidence indicates that odontogenic-associated maxillary sinus fungus ball (MSFB) should be distinguished from classical odontogenic sinusitis because the underlying dental abnormalities and therapeutic implications may differ. Another diagnostic challenge is the limited sensitivity of fungal culture. Viable fungal organisms may not always be recovered from mature fungal concretions; therefore, negative culture does not exclude fungus ball [4,11]. Histopathological examination is particularly important when available because demonstration of fungal elements without tissue invasion supports the diagnosis and distinguishes fungus ball from invasive fungal rhinosinusitis.
Endoscopic sinus surgery (ESS) is the treatment of choice for symptomatic PSFB [4]. Surgery aims to achieve complete clearance of fungal material and retained secretions, restore sinus ventilation and drainage, and preserve viable mucosa whenever possible. Routine systemic antifungal therapy is generally unnecessary after adequate surgical clearance of uncomplicated non-invasive disease [4].
The objective of the present case series was to describe the clinical presentation, CT characteristics, histopathological and mycological findings, and surgical management of five patients with unilateral maxillary sinus disease highly suggestive of MSFB, with particular emphasis on intralesional calcification, culture-negative disease, and the potential odontogenic contribution.
Case Series
Patients and Diagnostic Assessment
Five patients with persistent sinonasal symptoms and clinical and radiological findings suggestive of MSFB underwent endoscopic sinus surgery.
Available data regarding age, sex, presenting symptoms, previous medical treatment, relevant medical history, nasal endoscopy, CT characteristics, histopathological examination, fungal culture, and surgical procedure were reviewed.
The patients ranged from 29 to 66 years of age. All five lesions were unilateral and localized to the maxillary sinus. The main clinical, radiological, pathological, and surgical characteristics are summarized in (Table 1).
Case 1
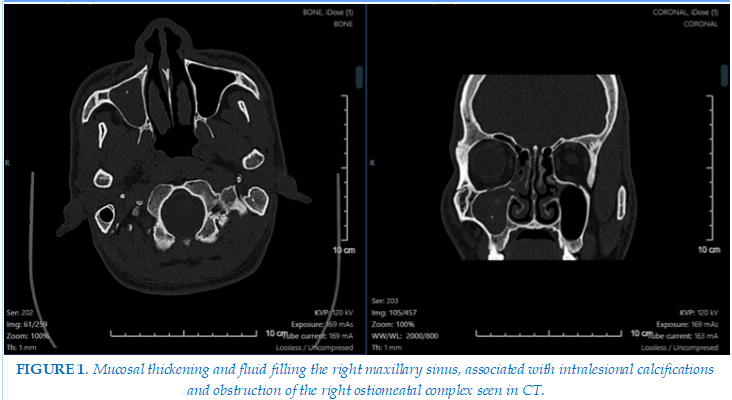
A 29-year-old man presented with headache, nasal discharge, and pressure over the right nasal and maxillary regions radiating toward the right orbit. He had previously received outpatient medical treatment without significant clinical improvement.
CT demonstrated mucosal thickening and fluid filling the right maxillary sinus, associated with intralesional calcifications and obstruction of the right ostiomeatal complex (Figure 1). These findings raised suspicion of a right MSFB.
The patient underwent right endoscopic maxillary sinus surgery. Histopathological examination of the surgical specimen demonstrated acute hyperemic inflammatory tissue.
Case 2
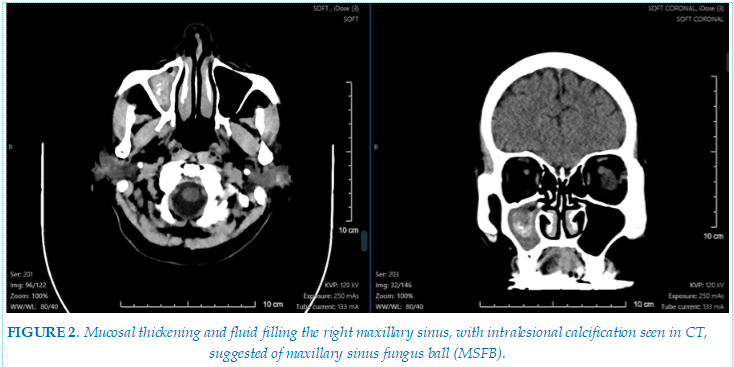
A 60-year-old woman presented with persistent right-sided purulent nasal discharge despite several courses of outpatient medical therapy. She had no significant previous medical history. CT demonstrated mucosal thickening and fluid filling the right maxillary sinus, with intralesional calcification suggestive of MSFB (Figure 2). The patient underwent right endoscopic maxillary sinus surgery. Material obtained intraoperatively was submitted for fungal culture, which yielded no fungal growth.
Case 3
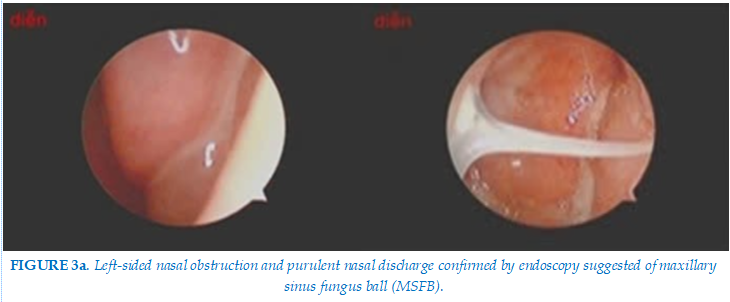
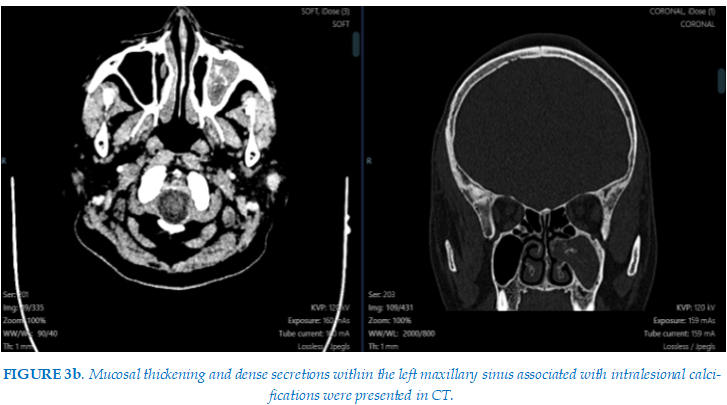
A 57-year-old woman presented with left-sided nasal obstruction, purulent nasal discharge, and headache (Figure 3a). She had previously received multiple courses of outpatient medical treatment without satisfactory improvement. Her medical history included pseudophakia following cataract surgery and glaucoma. CT demonstrated mucosal thickening and dense secretions within the left maxillary sinus associated with intralesional calcifications. (Figure 3b). The patient underwent left endoscopic maxillary sinus surgery. Fungal culture of the intraoperative specimen was negative.
Case 4
A 66-year-old man presented with headache accompanied by left-sided purulent nasal discharge. He had no significant previous medical history.
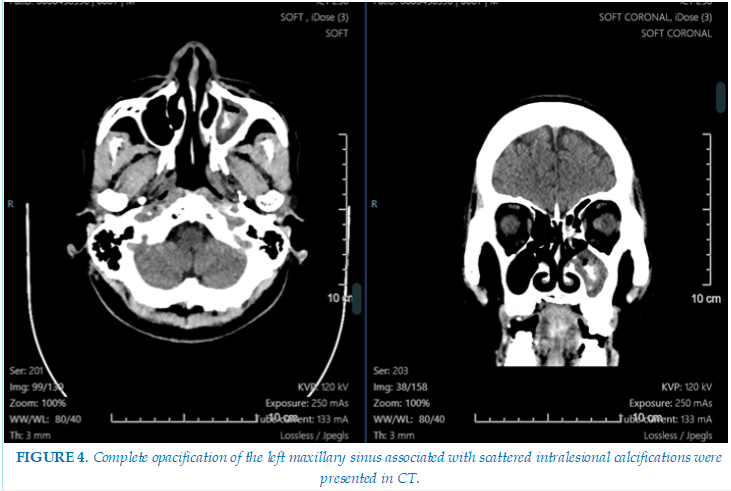
CT demonstrated complete opacification of the left maxillary sinus associated with scattered intralesional calcifications (Figure 4). Nasal endoscopy revealed abundant purulent secretion within the left middle meatus. The patient underwent endoscopic maxillary sinus surgery. Fungal culture of the material obtained from the maxillary sinus was negative.
Case 5
A 48-year-old woman presented with headache associated with right-sided purulent nasal discharge. She had no significant previous medical history.
CT demonstrated mucosal thickening of the right maxillary sinus associated with intralesional calcifications, raising suspicion of fungal sinus disease. (Figure 5).
The patient underwent right endoscopic maxillary sinus surgery. Fungal culture of the intraoperative specimen was positive for filamentous fungi.
Discussion
Clinical Presentation: The Importance of Persistent Unilateral Disease
The present case series illustrates an important feature of MSFB: the discrepancy between its relatively non-specific clinical manifestations and its more characteristic radiological appearance. All five patients had unilateral maxillary sinus involvement. Purulent nasal discharge and headache were the predominant manifestations, while nasal obstruction and facial or maxillary pressure were also observed.
These findings are consistent with previous series showing that PSFB generally presents as a single-sinus disease in middle-aged and older adults, with the maxillary sinus being the predominant location [4–6,12]. A recent phenotyping study of sinonasal Aspergillus disease also demonstrated that fungus ball predominantly occurs as single-sinus disease in older patients, contrasting with invasive fungal rhinosinusitis, which is more strongly associated with immunocompromised states [12].
Several patients in our series had received repeated courses of medical therapy without satisfactory improvement. Persistent unilateral symptoms despite conventional treatment should therefore prompt further evaluation rather than repeated empirical antimicrobial therapy. From a practical perspective, unilateral disease should encourage careful nasal endoscopy and CT assessment to distinguish MSFB from unilateral chronic rhinosinusitis, odontogenic sinusitis, retained foreign material, mucocele, and sinonasal neoplasia.
Intralesional Hyperattenuation and Calcification as Major CT Clues
The most consistent radiological feature in our series was intralesional calcification. All five patients demonstrated calcified or hyperattenuating foci within a partially or completely opacified maxillary sinus. Intralesional hyperattenuation is among the most recognized CT characteristics of PSFB [7,8,10]. Lee et al. demonstrated that CT findings can help differentiate maxillary sinus fungus ball from other causes of unilateral maxillary sinus disease [8]. Earlier imaging studies similarly established the characteristic appearance of hyperattenuating or calcified material within the involved sinus [7].
More recent studies have refined the interpretation of these hyperdensities. Alharbi et al. evaluated 64 patients with histologically or mycologically diagnosed maxillary or sphenoid fungus ball and identified hyperdensities in 63 cases. Metal-type hyperdensities were found exclusively in maxillary fungus balls and were significantly associated with endodontic treatment on the affected side [10]. These observations suggest that the nature and distribution of CT hyperdensities may provide information not only about the probability of fungus ball but also about potential odontogenic contributions. Nevertheless, intralesional calcification is an important diagnostic clue rather than a stand-alone diagnostic criterion.
The radiological pattern should always be interpreted in conjunction with clinical manifestations, nasal endoscopy, operative findings, histopathology, and mycology [4].
Negative Fungal Culture Does Not Exclude Fungus Ball
An important observation in this series was the high frequency of negative fungal cultures. Of four patients with available mycological testing, three had negative cultures and only one yielded filamentous fungi. Culture negativity in PSFB is well recognized. Dellière et al. demonstrated a substantial discrepancy between direct fungal examination and conventional culture in fungal ball rhinosinusitis, illustrating the limited sensitivity of culture alone [11].
Several mechanisms may contribute to negative cultures, including reduced viability of fungal organisms within mature concretions, sampling limitations, specimen transport and processing conditions, and prior alteration of the local sinus environment. Consequently, negative fungal culture should not be interpreted as evidence against MSFB when the clinical, CT, and operative features are strongly suggestive [4,11]. Conversely, a positive culture identifies viable fungi but does not establish whether tissue invasion is present. This distinction emphasizes the complementary role of histopathology. Demonstration of fungal hyphae together with absence of mucosal, vascular, or osseous invasion supports non-invasive fungus ball, whereas identification of tissue invasion fundamentally changes the diagnosis and management [2–4].
Importance of Histopathological Confirmation
A limitation of the present series is the lack of uniform histopathological assessment. Histopathological examination was documented in one patient and demonstrated acute hyperemic inflammatory tissue, whereas mycological culture was performed in the other reported cases. International consensus emphasizes that diagnosis of PSFB should integrate clinical, radiological, intraoperative, histopathological, and microbiological evidence [4]. Histopathological examination is particularly valuable because it can demonstrate fungal elements and, critically, exclude fungal invasion into sinonasal tissues. For future cases, all surgically removed material should therefore undergo systematic histopathological examination, including fungal-specific staining when indicated. This would strengthen diagnostic certainty and allow direct comparison between histopathological and mycological findings. The lack of uniform histopathological confirmation also means that the present series should be interpreted as five cases with a clinicoradiological diagnosis highly suggestive of MSFB, rather than five uniformly histologically proven cases.
The Odontogenic Dimension of Maxillary Sinus Fungus Ball
The exclusive maxillary localization observed in this series raises the clinically important question of odontogenic contribution. The anatomical proximity between posterior maxillary teeth and the maxillary sinus provides a potential relationship between dental disease or procedures and maxillary sinus pathology. Şahin et al. demonstrated a significant association between dental pathology or previous dental treatment and maxillary sinus fungus ball [9].
Alharbi et al. further demonstrated that metal-type CT hyperdensities in maxillary fungus balls were associated with previous endodontic treatment [10]. Recent evidence strengthens this concept while also emphasizing that MSFB and odontogenic sinusitis are related but distinct entities. In an international multicenter study, Im et al. compared 203 patients with MSFB with 163 patients with odontogenic sinusitis. Among the MSFB group, 141 had associated odontogenic conditions. The fungus-ball side was significantly associated with protrusion of root-canal treatment materials and dental implants [15].
By contrast, odontogenic sinusitis was more strongly associated with infectious dental conditions such as apical periodontitis and oroantral fistula [15]. This distinction has direct clinical relevance because infectious dental disease may require simultaneous dental treatment. Di Donna et al. similarly examined surgically treated chronic maxillary sinusitis according to odontogenic origin and the presence or absence of fungus ball, further highlighting the need to consider the dental–sinus relationship when managing unilateral maxillary sinus disease [14].
Accordingly, patients with suspected MSFB should undergo systematic review of the maxillary dentition and tooth–sinus interface on CT. Relevant dental history should include previous root-canal therapy, dental implants, dental extractions, and other procedures involving the posterior maxilla. Dental history was not systematically documented in the present series, which represents an important limitation and a priority for future prospective investigation.
Endoscopic Sinus Surgery as Definitive Management
Endoscopic sinus surgery is the established treatment for symptomatic PSFB [4–6]. Its objectives include complete removal of fungal concretions and retained secretions, restoration of sinus drainage and ventilation, adequate visualization of the affected sinus, and preservation of healthy mucosa whenever possible.
All five patients in our series underwent endoscopic maxillary sinus surgery. For maxillary disease, enlargement of the natural ostium through a middle meatal approach generally provides access for remov al and irrigation. However, anatomical location of the fungal material may influence surgical accessibility.
Kim et al. analyzed 221 patients with MSFB according to radiological localization and examined the relationship between disease location, surgical approach, and postoperative outcomes [13]. Their findings highlight the importance of preoperative CT not only for diagnosis but also for planning adequate access to the entire fungal burden. (PubMed Central (PMC)).
The Young-IFOS consensus identifies PSFB as a surgically treatable non-invasive mycosis and provides consensus recommendations regarding diagnosis, treatment indications, surgical management, and follow-up [4]. Because uncomplicated fungus ball is non-invasive and confined to the sinus lumen, routine systemic antifungal therapy is generally unnecessary after complete surgical clearance [4]. This differs fundamentally from invasive fungal rhinosinusitis, in which urgent surgical debridement and systemic antifungal therapy are required.
Clinical Implications for Unilateral Maxillary Sinus Disease
Taken together, our observations and current evidence support a practical diagnostic approach to persistent unilateral maxillary sinus disease.
First, persistent unilateral symptoms, particularly purulent nasal discharge, headache, obstruction, or facial pressure that fail to respond to conventional therapy, should prompt nasal endoscopy and CT rather than repeated empirical treatment. Second, unilateral maxillary sinus opacification associated with intralesional hyperattenuation or calcification should raise strong suspicion of MSFB [7,8,10]. Third, the CT examination should extend beyond the sinus itself to the maxillary dentition and sinus floor, particularly searching for root-canal filling material, implants, periapical disease, oroantral communication, or other odontogenic abnormalities [9,10,14,15]. Fourth, surgical material should ideally undergo both histopathological and mycological examination. A negative culture should not override characteristic clinicoradiological and histopathological findings [4,11]. Finally, ESS provides both definitive treatment and the opportunity to establish the diagnosis more securely through direct examination and tissue sampling.
Limitations
This case series has several limitations. First, the small sample size and descriptive design limit generalizability. Second, histopathological and mycological investigations were not standardized across all patients. Third, the available records did not systematically document intraoperative characteristics of fungal material. Fourth, dental history and odontogenic risk factors were not prospectively assessed despite the exclusive maxillary localization of disease. Fifth, validated patient-reported outcome measures such as the 22-item Sinonasal Outcome Test (SNOT-22) were unavailable. Finally, duration of postoperative follow-up and objective endoscopic outcomes were not standardized.
These limitations suggest priorities for future prospective studies, including systematic histopathological confirmation, standardized fungal identification, detailed dental evaluation, structured radiological assessment, validated sinonasal symptom scores, and predefined postoperative follow-up.
Conclusions
Maxillary sinus fungus ball should be considered in patients with persistent unilateral maxillary sinus disease, particularly when symptoms fail to improve with conventional medical treatment. In this five-patient series, all lesions were unilateral and all CT examinations demonstrated intralesional calcification within the affected maxillary sinus. This consistent finding reinforces the diagnostic importance of intralesional hyperattenuation or calcification, although CT findings alone cannot establish a definitive diagnosis.
Negative fungal culture does not exclude MSFB. Accurate diagnosis requires integration of clinical manifestations, nasal endoscopy, CT findings, intraoperative appearance, histopathological assessment, and mycological examination.
The potential odontogenic contribution should be systematically assessed in maxillary disease, particularly in patients with previous root-canal treatment, dental implants, or abnormalities of the tooth–sinus interface. Endoscopic sinus surgery remains the treatment of choice for symptomatic MSFB, allowing complete clearance of pathological sinus contents, restoration of sinus ventilation and drainage, and acquisition of material for histopathological and mycological assessment. Clinically, persistent unilateral maxillary sinus opacification associated with intralesional hyperattenuation or calcification should prompt consideration of MSFB, even when fungal culture is negative.
REFERENCES
| 1. Fokkens, W.J.; Lund, V.J.; Hopkins, C.; Hellings, P.W.; Kern, R.; Reitsma, S.; Toppila-Salmi, S.; Bernal-Sprekelsen, M.; Mullol, J.; Alobid, I.; et al. European Position Paper on Rhinosinusitis and Nasal Polyps 2020. Rhinology 2020, 58 (Suppl. S29), 1–464. |
| 2. Deutsch, P.G.; Whittaker, J.; Prasad, S. Invasive and non-invasive fungal rhinosinusitis—A review and update of the evidence. Medicina 2019, 55, 319. |
| 3. Chakrabarti, A.; Denning, D.W.; Ferguson, B.J.; Ponikau, J.; Buzina, W.; Kita, H.; Marple, B.; Panda, N.; Vlaminck, S.; Kauffmann-Lacroix, C.; et al. Fungal rhinosinusitis: A categorization and definitional schema addressing current controversies. Laryngoscope 2009, 119, 1809–1818. |
| 4. Saibene, A.M.; Allevi, F.; Calvo-Henriquez, C.; Dauby, N.; Dondossola, D.; Hervochon, R.; et al. Comprehensive management of paranasal sinus fungus balls: A Young-IFOS consensus statement. Int. Forum Allergy Rhinol. 2023, 13, 877–885. |
| 5. Yoon, Y.H.; Xu, J.; Park, S.K.; Heo, J.H.; Kim, Y.M.; Rha, K.S. A retrospective analysis of 538 sinonasal fungus ball cases treated at a single tertiary medical center in Korea (1996–2015). Int. Forum Allergy Rhinol. 2017, 7, 1070–1075. |
| 6. Nicolai, P.; Lombardi, D.; Tomenzoli, D.; Villaret, A.B.; Piccioni, M.; Mensi, M.; Maroldi, R. Fungus ball of the paranasal sinuses: Experience in 160 patients treated with endoscopic surgery. Laryngoscope 2009, 119, 2275–2279. |
| 7. Zinreich, S.J.; Kennedy, D.W.; Malat, J.; Curtin, H.D.; Epstein, J.I.; Huff, L.C.; Kumar, A.J.; Johns, M.E.; Rosenbaum, A.E. Fungal sinusitis: Diagnosis with CT and MR imaging. Radiology 1988, 169, 439–444. |
| 8. Lee, D.H.; Yoon, T.M.; Lee, J.K.; Lim, S.C. Computed tomography-based differential diagnosis of fungus balls in the maxillary sinus. Oral Surg. Oral Med. Oral Pathol. Oral Radiol. 2020, 129, 277–281. |
| 9. Şahin, B.; Çomoğlu, Ş.; Sönmez, S.; Değer, K.; Keleş Türel, M.N. Paranasal sinus fungus ball, anatomical variations and dental pathologies: Is there any relation? Turk. Arch. Otorhinolaryngol. 2022, 60, 23–28. |
| 10. Alharbi, A.; Reville, N.; Molinier, S.; Bastier, P.L.; de Gabory, L. Characterization of fungus ball CT-hyperdensities within maxillary and sphenoid sinuses. Dentomaxillofac. Radiol. 2022, 51, 20180384. |
| 11. Dellière, S.; Dannaoui, E.; Fieux, M.; Bonfils, P.; Gricourt, G.; Demontant, V.; Podglajen, I.; Woerther, P.L.; Angebault, C.; Botterel, F. Analysis of microbiota and mycobiota in fungal ball rhinosinusitis: Specific interaction between Aspergillus fumigatus and Haemophilus influenzae? J. Fungi 2021, 7, 550. |
| 12. Hafrén, L.; Saarinen, R.; Kurimo, R.; Viljanen, M.; Lundberg, M. Aspergillus sinusitis: Risk factors and phenotyping. J. Clin. Med. 2024, 13, 2579. |
| 13. Kim, D.H.; Kown, J.H.; Koo, H.B.; Lee, J.H. Clinical characteristics according to the radiological classifications of maxillary sinus fungus ball. J. Rhinol. 2022, 29, 32–37. |
| 14. Di Donna, E.; Perez, A.; Hsieh, J.W.; Daskalou, D.; Aymon, R.; Landis, B.N.; Scolozzi, P. Surgically treated chronic maxillary sinusitis: Does the odontogenic etiology alone or in combination with a fungus ball matter? J. Stomatol. Oral Maxillofac. Surg. 2025, 126, 102086. |
| 15. Im, E.; Donaldson, L.; Adelman, A.; Adappa, N.D.; Chen, Y.W.; Chapurin, N.; Douglas, J.E.; et al. Clinical features and dental pathologies in maxillary sinus fungal balls and odontogenic sinusitis. Laryngoscope 2026, 136, 2913–2924. |

TABLE - FIGURES


REFERENCES
| 1. Fokkens, W.J.; Lund, V.J.; Hopkins, C.; Hellings, P.W.; Kern, R.; Reitsma, S.; Toppila-Salmi, S.; Bernal-Sprekelsen, M.; Mullol, J.; Alobid, I.; et al. European Position Paper on Rhinosinusitis and Nasal Polyps 2020. Rhinology 2020, 58 (Suppl. S29), 1–464. |
| 2. Deutsch, P.G.; Whittaker, J.; Prasad, S. Invasive and non-invasive fungal rhinosinusitis—A review and update of the evidence. Medicina 2019, 55, 319. |
| 3. Chakrabarti, A.; Denning, D.W.; Ferguson, B.J.; Ponikau, J.; Buzina, W.; Kita, H.; Marple, B.; Panda, N.; Vlaminck, S.; Kauffmann-Lacroix, C.; et al. Fungal rhinosinusitis: A categorization and definitional schema addressing current controversies. Laryngoscope 2009, 119, 1809–1818. |
| 4. Saibene, A.M.; Allevi, F.; Calvo-Henriquez, C.; Dauby, N.; Dondossola, D.; Hervochon, R.; et al. Comprehensive management of paranasal sinus fungus balls: A Young-IFOS consensus statement. Int. Forum Allergy Rhinol. 2023, 13, 877–885. |
| 5. Yoon, Y.H.; Xu, J.; Park, S.K.; Heo, J.H.; Kim, Y.M.; Rha, K.S. A retrospective analysis of 538 sinonasal fungus ball cases treated at a single tertiary medical center in Korea (1996–2015). Int. Forum Allergy Rhinol. 2017, 7, 1070–1075. |
| 6. Nicolai, P.; Lombardi, D.; Tomenzoli, D.; Villaret, A.B.; Piccioni, M.; Mensi, M.; Maroldi, R. Fungus ball of the paranasal sinuses: Experience in 160 patients treated with endoscopic surgery. Laryngoscope 2009, 119, 2275–2279. |
| 7. Zinreich, S.J.; Kennedy, D.W.; Malat, J.; Curtin, H.D.; Epstein, J.I.; Huff, L.C.; Kumar, A.J.; Johns, M.E.; Rosenbaum, A.E. Fungal sinusitis: Diagnosis with CT and MR imaging. Radiology 1988, 169, 439–444. |
| 8. Lee, D.H.; Yoon, T.M.; Lee, J.K.; Lim, S.C. Computed tomography-based differential diagnosis of fungus balls in the maxillary sinus. Oral Surg. Oral Med. Oral Pathol. Oral Radiol. 2020, 129, 277–281. |
| 9. Şahin, B.; Çomoğlu, Ş.; Sönmez, S.; Değer, K.; Keleş Türel, M.N. Paranasal sinus fungus ball, anatomical variations and dental pathologies: Is there any relation? Turk. Arch. Otorhinolaryngol. 2022, 60, 23–28. |
| 10. Alharbi, A.; Reville, N.; Molinier, S.; Bastier, P.L.; de Gabory, L. Characterization of fungus ball CT-hyperdensities within maxillary and sphenoid sinuses. Dentomaxillofac. Radiol. 2022, 51, 20180384. |
| 11. Dellière, S.; Dannaoui, E.; Fieux, M.; Bonfils, P.; Gricourt, G.; Demontant, V.; Podglajen, I.; Woerther, P.L.; Angebault, C.; Botterel, F. Analysis of microbiota and mycobiota in fungal ball rhinosinusitis: Specific interaction between Aspergillus fumigatus and Haemophilus influenzae? J. Fungi 2021, 7, 550. |
| 12. Hafrén, L.; Saarinen, R.; Kurimo, R.; Viljanen, M.; Lundberg, M. Aspergillus sinusitis: Risk factors and phenotyping. J. Clin. Med. 2024, 13, 2579. |
| 13. Kim, D.H.; Kown, J.H.; Koo, H.B.; Lee, J.H. Clinical characteristics according to the radiological classifications of maxillary sinus fungus ball. J. Rhinol. 2022, 29, 32–37. |
| 14. Di Donna, E.; Perez, A.; Hsieh, J.W.; Daskalou, D.; Aymon, R.; Landis, B.N.; Scolozzi, P. Surgically treated chronic maxillary sinusitis: Does the odontogenic etiology alone or in combination with a fungus ball matter? J. Stomatol. Oral Maxillofac. Surg. 2025, 126, 102086. |
| 15. Im, E.; Donaldson, L.; Adelman, A.; Adappa, N.D.; Chen, Y.W.; Chapurin, N.; Douglas, J.E.; et al. Clinical features and dental pathologies in maxillary sinus fungal balls and odontogenic sinusitis. Laryngoscope 2026, 136, 2913–2924. |
ARTICLE INFO DOI: 10.12699/jfvpulm.17.54.2026.06
Conflict of Interest
Non
Date of manuscript receiving
25/06/2026
Date of publication after correction
6/10/2026
Article citation
Diep Le-Van, Trang Nguyen-Minh, Hien Duong-Thi-Thu, Khanh Le-Xuan, Anh Luu-Thi-Van, Chung Tran-Nam, Phap Tran-Quang, Tuyen Hoang-Thanh, Sy Duong-Quy. Maxillary Sinus Fungus Ball: Clinical Presentation, Computed Tomography Features, and Surgical Management: A Five-Patient Case Series. J Func Vent Pulm 2026;54(17):17-22


